
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
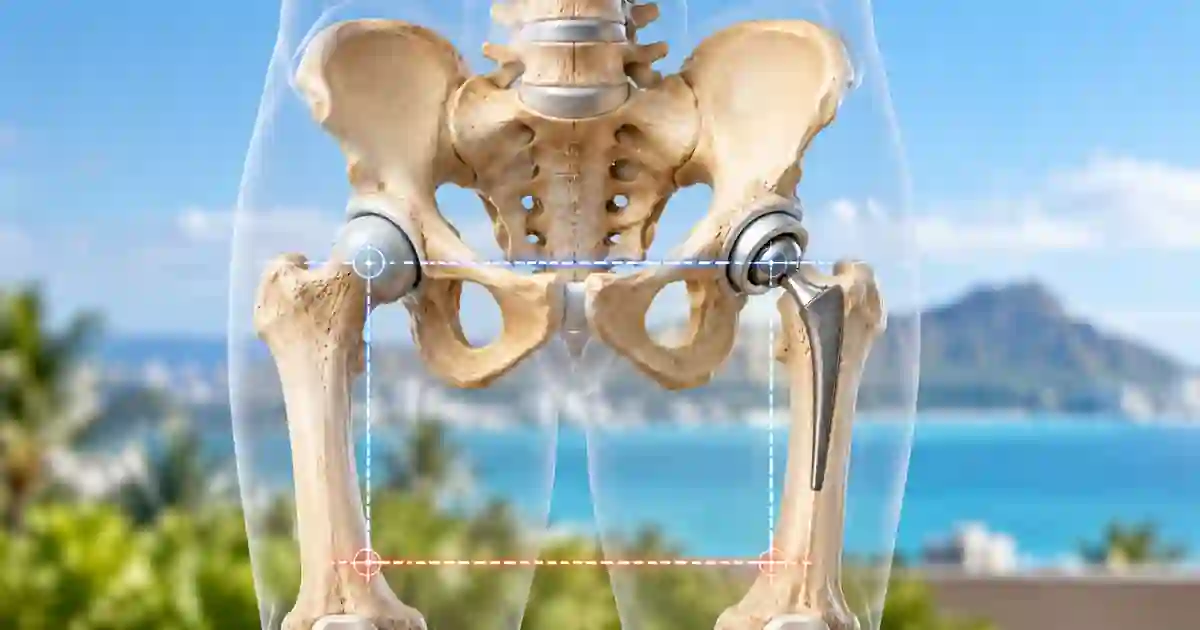
Two different problems can feel exactly the same
When patients say one leg feels longer after total hip replacement, there are two broad possibilities. A structural leg-length difference means the bony relationship between the pelvis and femur is actually different. A functional or apparent difference means the bones may be similar in length, but pelvic tilt, spinal alignment, muscle contracture, weakness, or the way the patient stands creates the sensation of unequal legs.
This distinction matters because early functional differences are common and often improve as swelling settles, muscles recover, and the pelvis gradually rebalances. A 2025 review emphasized that clinical examination and imaging should be considered together because radiographs alone do not explain every patient's symptoms. 2025 review of leg-length discrepancy after total hip arthroplasty.
Why surgeons cannot simply make both legs mathematically identical
Restoring length is important, but hip replacement is not only a leg-length operation. The surgeon also has to restore hip stability, offset, soft-tissue tension, implant position, and the center of rotation. In some cases, forcing exact symmetry could compromise another part of the reconstruction.
That is why experienced hip surgeons plan for the best overall biomechanics rather than promising perfectly equal numbers. Orthopedic literature has long emphasized that equal leg length cannot be guaranteed after total hip arthroplasty and that stability and safe reconstruction remain essential priorities. JAAOS review of leg-length discrepancy after THA.
Why the replaced side may feel longer during the first few weeks
Before surgery, an arthritic hip can shorten through cartilage loss, bone wear, fixed flexion or adduction contracture, and pelvic compensation. The body may spend months or years adapting to that position. When the joint is reconstructed, the pelvis and muscles do not instantly forget the old posture.
Early after surgery, several factors can create the feeling that the operated leg is longer even when radiographs show only a small difference:
- Pelvic obliquity: the pelvis may still be tilted from years of guarding or arthritis.
- Muscle tightness: hip flexors, abductors, adductors, and the lower back can remain asymmetric early in recovery.
- Spinal alignment: scoliosis or a stiff lumbar spine can change the apparent relationship between the pelvis and legs.
- Swelling and weakness: postoperative swelling and altered gait can exaggerate the sensation.
- Correction of a preoperative short leg: returning the hip closer to its intended anatomy can initially feel like over-lengthening because the body had adapted to being short.
How leg length is checked before and during surgery
Good planning starts before the operation. Surgeons compare the pelvis, hip center, femoral anatomy, offset, and pre-existing limb-length difference on standing examination and imaging. During surgery, leg length can be assessed with anatomic landmarks, fluoroscopy, navigation, or robotic planning depending on the technique and equipment used.
Direct anterior hip replacement is often performed with the patient lying on the back, which can make fluoroscopic comparison of the pelvis and both hips practical during the operation. A 2024 systematic review of 29 studies examined leg-length discrepancy with the direct anterior approach and described multiple strategies for controlling length intraoperatively. 2024 systematic review of direct anterior THA and leg length.
Can robotic assistance improve leg-length accuracy?
Robotic and computer-assisted systems can provide additional measurements for implant position, offset, and planned leg length. That can improve the information available to the surgeon, but it does not replace judgment about stability, bone quality, and soft-tissue tension.
A 2026 systematic review and meta-analysis of seven comparative studies involving 968 patients reported a smaller average postoperative leg-length discrepancy with robot-assisted total hip arthroplasty than with conventional surgery. The reported mean difference was about 2 mm. That is encouraging, but it should not be interpreted as a guarantee that every robotic hip will have perfectly equal leg lengths or that a 2 mm average difference is clinically meaningful for every patient. 2026 meta-analysis of robotic THA and leg length.
How much difference is too much?
There is no single number at which every patient becomes symptomatic. Older reviews often cite differences under about 10 mm as commonly tolerated, but symptoms do not follow a ruler perfectly. Some patients notice a small difference, while others adapt well to a larger one. The direction of the discrepancy, pelvic alignment, spinal disease, muscle function, and the patient's gait all influence whether it becomes a problem.
The more useful question is whether the difference is persistent, measurable, and causing functional problems such as a limp, back pain, instability, difficulty walking, or a need for a shoe lift. A current review published in 2025 noted that reported leg-length differences after THA vary widely across studies because measurement methods and patient populations differ. Review of clinical and imaging assessment after THA.
Do not rush to a shoe lift in the first few weeks
If the hip is stable and the difference is mainly functional, immediately adding a permanent shoe lift can sometimes reinforce a temporary pelvic position before the body has had time to adapt. Early treatment usually focuses on safe walking, restoring hip and core strength, correcting gait mechanics, and allowing contractures and pelvic tilt to settle.
That does not mean every patient should wait indefinitely. A large or clearly structural discrepancy may deserve earlier evaluation. The point is that a lift should be based on a measured, persistent problem rather than the first few days of postoperative sensation.
When persistent leg-length symptoms deserve imaging
If the sensation remains strong after the early recovery period, or if it is associated with significant limp, back pain, nerve symptoms, instability, or difficulty walking, the evaluation should go beyond simply measuring from the hip to the ankle with a tape measure.
The workup may include a standing examination of pelvic tilt, gait assessment, review of preoperative and postoperative X-rays, and sometimes longer-leg or spine imaging when the source is unclear. The goal is to determine whether the issue is coming from the reconstructed hip, the pelvis, the spine, or a combination of factors.
When revision surgery is considered
Most patients with an early sense of unequal leg length do not need another operation. Conservative treatment is especially appropriate when the implants are well positioned, the hip is stable, and the discrepancy is functional or modest.
Revision becomes a discussion when there is a substantial persistent structural discrepancy that causes meaningful disability, when implant position contributes to instability or nerve symptoms, or when another mechanical problem is present. Revision surgery carries its own risks, so the decision should be based on symptoms, imaging, implant position, and the likely benefit of correction rather than a number alone. Patients with a painful or mechanically concerning hip replacement can review the revision hip replacement guide.
What to ask before hip replacement
Leg-length planning is worth discussing before surgery, especially if you already know one leg is shorter, have scoliosis, have had prior hip or femur surgery, or use a shoe lift.
- Do I already have a true or apparent leg-length difference before surgery?
- Is my pelvis tilted because of hip contracture or spinal alignment?
- How will leg length and offset be assessed during the operation?
- Does my anatomy create a tradeoff between equal length and hip stability?
- If the leg feels longer after surgery, when should it be re-measured?
- At what point would physical therapy, a temporary lift, additional imaging, or a second evaluation be useful?
The practical takeaway
A hip that feels longer after replacement is not automatically a surgical error, and the sensation does not always represent a true bony difference. Early pelvic tilt and muscle adaptation are common. At the same time, a persistent structural discrepancy can affect gait and comfort and deserves a careful evaluation.
The best approach is to establish the starting anatomy, plan the reconstruction carefully, measure during surgery, and reassess persistent symptoms after the early recovery phase. If you are planning a primary hip replacement, the hip replacement guide explains the overall surgical and recovery pathway.
Sources and further reading
- Bianco Prevot L, et al. Leg Length Discrepancy After Total Hip Arthroplasty: A Review of Clinical Assessments, Imaging Diagnostics, and Medico-Legal Implications. 2025.
- Tassinari L, et al. Leg length discrepancy after total hip arthroplasty performed by direct anterior approach: a systematic review. 2024.
- Robotic assistance in total hip arthroplasty: systematic review and meta-analysis of leg length, cup orientation, and early outcomes. 2026.
- Gheewala RA, et al. Perioperative management of leg-length discrepancy in total hip arthroplasty: a review. 2023.
Medically reviewed by Paul Norio Morton, MD, FAAOS, FAAHKS. Last reviewed: . This article is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.