
 English
 日本語
 한국어
 中文(廣東話)
 Tagalog
 ไทย
 Tiếng Việt
 Chuukese
Meniscus repair surgery in Honolulu — the short answer
Meniscus surgery is arthroscopic: a repairable tear is sutured so it heals, or an unrepairable fragment is trimmed to a stable rim. Repair suits red-zone tears and younger, active knees, including tears found with an ACL injury. Dr. Morton repairs whenever the biology allows, trims conservatively when it doesn't, and says plainly when a degenerative tear in an arthritic knee won't benefit from a scope. Individual results vary.
- Outpatient arthroscopy under general or regional anesthesia, often under an hour — home the same day
- Repair: 3–5 months of protected recovery, but your shock absorber survives; partial meniscectomy: walking the same day, most activities within weeks
- Degenerative tears: randomized trials found arthroscopy no better than physical therapy or sham surgery — so surgery is reserved for specific situations
- PRP augmentation is available for borderline repairs; the evidence is mixed and it is an optional cash-pay add-on
- Four clinics — Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo, Kona — with same-week injury access through Wiki Wiki Orthopedics
Are you a candidate for meniscus surgery?
Surgery treats symptoms and protects the knee — it does not treat an MRI report. Based on the exam, X-rays, and MRI, surgery is worth discussing if:
- Your knee is truly locked — stuck and unable to fully straighten — from a displaced bucket-handle or flap tear; this deserves prompt arthroscopy
- You have a large or displaced tear in a young or active knee, where preserving tissue matters for decades
- Mechanical symptoms persist — catching, giving way, recurrent swelling — despite a genuine course of physical therapy and activity modification
- The tear travels with an ACL injury: repairable tears become unrepairable with time and instability, so it is fixed at the same operation
- It may not be the right move if: the tear is degenerative in a knee with arthritis and the main symptom is pain; the MRI shows a tear but your knee functions well; or an acute injury is still settling — quad strengthening and time often do the job
Knee anatomy: why the menisci matter
Meniscus tears are one of the most common sources of knee pain, and there are reliable ways to figure out whether you have one — and to protect the knee before a tear causes lasting damage.
The knee joins the thigh bone (femur) to the two bones of the lower leg (tibia and fibula), each surface coated in smooth articular cartilage so the joint glides without pain. Between the femur and tibia sit two additional pieces of cartilage that make the whole system work: the menisci. Each meniscus is a crescent-shaped wedge — the medial meniscus on the inner side of the knee, the lateral meniscus on the outer side. Together they spread load, absorb and dissipate the forces of every step, stabilize the knee during rotation, and help the joint move smoothly.
Lose meniscus tissue and the force on your articular cartilage concentrates dramatically — which is why meniscus loss is one of the strongest predictors of future knee arthritis. That single fact drives almost every decision on this page.
Acute vs. degenerative tears: two different problems
Because the menisci carry so much stress with every step, they are prone to injury — but not all tears are the same, and understanding which kind you have is the key to predicting how it will do.
Acute (traumatic) tears most often happen during a twisting motion: the foot is planted, the knee is flexed, and the body rotates over it. That combination puts a shearing force across the meniscus, and it tears. These injuries are common in pivoting sports — soccer, football, basketball — and frequently travel together with an ACL tear. Most people can still walk immediately afterward with a variable degree of pain; over the next 24 hours, swelling develops and the pain builds. Larger tears cause more pain and restrict knee motion, and a large displaced fragment can lock the knee outright. Left untreated, acute meniscus tears are associated with developing osteoarthritis later in life.
Degenerative tears occur in middle-aged and older adults, usually without a single injury — the tissue weakens over years of repetitive load until it tears with something as minor as a squat. Degenerative tears and osteoarthritis are closely intertwined: as arthritis develops, the meniscus becomes damaged and frayed, and the symptoms of the two — pain, stiffness, intermittent swelling — overlap heavily.
Mechanical symptoms: when a scope helps, and when it doesn't
That overlap matters for treatment. A knee that is truly locked — stuck and unable to straighten — usually needs prompt arthroscopy. Intermittent catching or clicking in an arthritic knee is a different story: in the FIDELITY trial's secondary analysis (Sihvonen et al., Annals of Internal Medicine 2016), patients with degenerative tears who reported catching or locking were no more likely to be rid of those symptoms after partial meniscectomy than after sham surgery. Pain alone is more likely coming from the arthritis itself — and a scope will not fix arthritis. Dr. Morton will tell you which situation you're in.
Tear patterns: the map that predicts healing
Surgeons describe meniscus tears by their pattern, because the pattern helps plan the treatment and predict its success. Tears may be vertical longitudinal, transverse, oblique, horizontal, meniscal root, bucket-handle, or complex (a combination of patterns).
Just as important is the tear's position on the meniscus's blood-supply map. The outer red zone has real circulation and therefore real healing potential; the inner white zone is essentially avascular, so sutures placed there rarely hold. As a rule, better blood supply means better healing — and a meniscus repaired at the same time as an ACL reconstruction tends to heal more reliably still, because the reconstruction bathes the joint in healing factors.
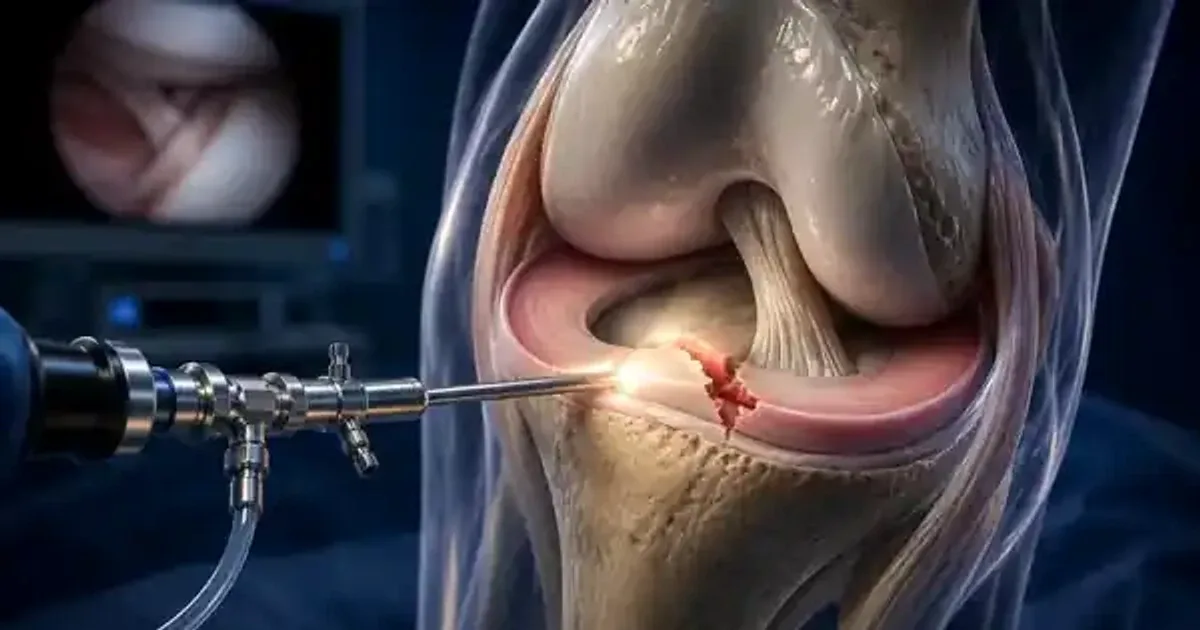
The final call is often made during surgery, once Dr. Morton can see the tear directly through the arthroscope. If the tissue has a realistic chance of healing, he will offer repair. If it genuinely cannot heal, the damaged fragment is removed — conservatively.
First aid and nonoperative care: many tears never need surgery
The first-line treatment for an acute meniscus tear is straightforward:
- Rest — avoid positions and activities that stress the joint, especially deep squatting and pivoting
- Ice — 15 minutes every 4–6 hours until the swelling resolves
- Elevation — keeping the leg up helps the swelling drain
- Quadriceps strengthening — once pain and swelling settle, gradually rebuild the quad; a strong quadriceps compensates for the stability the injured meniscus isn't providing
Repair vs. partial meniscectomy vs. no surgery
A meniscus repair sutures the torn tissue and anchors it in place so it can heal. A meniscectomy removes meniscus — in modern practice, almost always a partial meniscectomy that trims only the damaged, unrepairable fragment. And for many degenerative tears the right operation is none at all. Side by side:
| Meniscus repair | Partial meniscectomy | No surgery | |
|---|---|---|---|
| Best for | Red-zone and longitudinal tears, younger and active knees, tears found with an ACL injury | Unrepairable white-zone fragments, degenerate flaps, a locked knee that can't be repaired | Small stable tears; degenerative tears in arthritic knees; MRI tears in knees that function well |
| Tissue kept | All of it — the shock absorber survives | Trimmed to a stable rim; removed tissue never comes back | All of it |
| Weight-bearing | Protected early, often with a brace, while sutures heal | Walking the same day | As tolerated |
| Recovery | 3–5 months to return to sport | Desk work within days, most activities within weeks | Quad rehab over weeks; symptoms often settle |
| Long-term arthritis risk | Lowest if the repair heals | Rises with the amount removed; slightly greater X-ray progression at 5 years in the FIDELITY trial | Unchanged by surgery — driven by the knee itself |
How repairs are done — and why the rehab differs
How repairs are done. The meniscus's blood-supply zones drive the choice: the outer red zone heals, the inner white zone rarely does. Repairable tears are sutured through the arthroscope with all-inside devices, or with inside-out sutures tied through a small accessory incision for larger longitudinal and bucket-handle tears. A root tear — the meniscus pulled off its bony anchor — is re-anchored to the tibia, because a detached root unloads nothing and the knee behaves as if the meniscus were gone. When trimming is the honest answer, it is done conservatively; millimeters matter here.
Why the rehab differs. After a repair the sutured tissue must be protected while it heals — expect a brace, protected weight-bearing, and limits on deep bending early, with return to sport around 3–5 months. After a partial meniscectomy there is nothing to protect, so you walk the same day and progress as comfort allows. The longer path buys your knee decades; that trade is usually worth it in a young knee.
What the outcomes data show
The numbers explain the philosophy. Acute, traumatic tears in younger knees do well with surgery: whether the tear is repaired or trimmed, most patients return to sport or report being satisfied with the result. The honest caveat is that repairs do not always heal — across the published literature, roughly a quarter of isolated meniscus repairs fail and need a second procedure (a 2021 systematic review in Orthopaedic Journal of Sports Medicine) — which is why repair is chosen for tears with real healing potential, not for every tear.
Degenerative tears are a different story. Three randomized trials define the evidence: the sham-controlled FIDELITY trial (Sihvonen et al., NEJM 2013), METEOR (Katz et al., NEJM 2013), and ESCAPE (van de Graaf et al., JAMA 2018). In each, most patients with degenerative tears improved after arthroscopic partial meniscectomy — but they improved no more than patients treated with structured physical therapy or sham surgery at one to two years. FIDELITY's five-year follow-up also found slightly greater progression of X-ray arthritis in the surgery group. That is why managing a degenerative tear is usually a multi-pronged strategy — physical therapy, activity modification, and pain management — rather than a reflexive trip to the operating room, with surgery reserved for a truly locked knee or symptoms that persist despite real rehab. Honest patient selection is what keeps surgical results good.
PRP-augmented repair and the repair-first philosophy
Dr. Morton repairs tears whenever the pattern and biology give a repair a real chance — including borderline cases many surgeons would simply trim, because the long-term math favors preserved tissue. For borderline repairs, adding PRP at the suture line may improve the odds of healing by delivering concentrated growth factors to tissue that can't supply its own (more on PRP in meniscus repair).
The evidence is mixed, and it's framed that way: two meta-analyses of comparative studies (Orthopaedic Journal of Sports Medicine 2021; Journal of Orthopaedics 2025) found lower repair-failure rates with PRP augmentation, while a 2022 meta-analysis in the Journal of Orthopaedics and Traumatology found no difference in failure or function. PRP does not make an unrepairable tear repairable, it doesn't shorten the protected recovery, and most insurers don't cover it — so it is an optional cash-pay add-on, quoted before surgery, that you can take or leave. The repair itself is what matters most.
Surgery day, the pain plan, and recovery after repair
Meniscus surgery is same-day surgery under general or regional anesthesia, often taking under an hour. Long-acting local anesthetic is placed during surgery and every case is paired with an opioid-sparing multimodal pain plan, so narcotics play a minimal role. Expect one to two hours in the recovery room; then a loved one drives you home. After a partial meniscectomy you walk the day of surgery. After a repair, the arc looks like this:
- Surgery day
Outpatient arthroscopy
Small incisions, the tear sutured, home the same day with the knee wrapped, iced, and elevated.
- Early weeks
Protect the repair
Brace and protected weight-bearing on crutches while the sutured tissue knits; deep bending limited. Quad activation starts right away.
- Then
Motion and strength
Full extension and bend restored, then closed-chain strength work with PB&J Physical Therapy in Honolulu or Kunia, or a therapist near home.
- Months 3–5
Return to sport
Running, cutting, and pivoting return as strength and a quiet knee allow — earned, not scheduled.
The risks, stated plainly
Arthroscopic meniscus surgery is low-risk as operations go, and informed patients make better decisions. The possible complications include:
- Repair failure or re-tear — roughly a quarter of isolated repairs across the literature don't heal and need a second procedure, usually a partial meniscectomy; healing odds are best in red-zone tears and alongside an ACL reconstruction
- Stiffness — particularly after the protected phase of a repair; early motion within the protocol is the countermeasure
- Nerve irritation — numbness around the portals, and with inside-out repairs the saphenous nerve on the inner knee can be irritated
- Blood clots and infection — the baseline risks of any knee surgery, uncommon after arthroscopy
- Persistent pain — when arthritis, not the tear, was the real driver; this is why degenerative tears are triaged so carefully
- Arthritis after meniscectomy — removed tissue concentrates load on cartilage for life, which is the whole argument for repair-first
Recovery, by pathway
After repair: the sutured tissue must be protected while it heals — expect a brace and limited weight-bearing early, with return to sport around 3–5 months. After partial meniscectomy: walking the same day, desk work within days, and most activities within a few weeks. Either way, quad strengthening is your insurance policy, and follow-up tracks how the knee — and its long-term cartilage health — is actually doing. Physical therapy is available in-house through PB&J Physical Therapy at the Honolulu and Kunia clinics, working from Dr. Morton's rehabilitation protocols; neighbor island or traveling patients can structure evaluation by telehealth when an in-person visit isn't practical, with surgery on a planned O‘ahu trip. Uninsured? The practice offers bundled self-pay knee arthroscopy, quoted in writing. Cartilage damage found at surgery is treated on the same restoration ladder.
The bottom line — and how to get seen this week
The menisci absorb stress, stabilize the joint, and keep your knee moving smoothly — and once tissue is gone, it's gone. Treatment ranges from rest and rehab to suture repair, and the best option depends on your tear, your knee, and your goals. Dr. Morton sees meniscus patients at four clinics — Honolulu (Ala Moana), West O‘ahu (Kunia), Hilo, and Kona — and operates at The Queen's Medical Center and Adventist Health Castle.
A twisted knee that swelled or locked deserves eyes this week: book a consultation online or call (808) 439-6201, and on the Leeward side Wiki Wiki Orthopedics takes walk-ins with X-ray on site and hands off directly to Dr. Morton. Bring a photo ID, your insurance card, and any prior X-rays or MRI. Managed-care and Medicaid/Quest plans may require a referral from your primary care physician; the office checks before your visit. Already been told you need a meniscectomy? A second opinion on whether the tear can be saved is a reasonable ask before agreeing to remove tissue you can't get back.
References
- Sihvonen R, et al. Arthroscopic partial meniscectomy versus sham surgery for a degenerative meniscal tear. N Engl J Med. 2013;369:2515–2524. Source
- Sihvonen R, et al. Mechanical symptoms and arthroscopic partial meniscectomy in patients with degenerative meniscus tear: a secondary analysis of a randomized trial. Ann Intern Med. 2016;164(7):449–455. Source
- Sihvonen R, et al. Arthroscopic partial meniscectomy for a degenerative meniscus tear: a 5 year follow-up of the placebo-surgery controlled FIDELITY trial. Br J Sports Med. 2020;54(22):1332–1339. Source
- Katz JN, et al. Surgery versus physical therapy for a meniscal tear and osteoarthritis (METEOR). N Engl J Med. 2013;368:1675–1684. Source
- van de Graaf VA, et al. Effect of early surgery vs physical therapy on knee function among patients with nonobstructive meniscal tears: the ESCAPE randomized clinical trial. JAMA. 2018;320(13):1328–1337. Source
- Biologic augmentation reduces the failure rate of meniscal repair: a systematic review and meta-analysis. Orthop J Sports Med. 2021;9(2). Source
- Platelet-rich plasma augmentation does not result in more favourable outcomes in arthroscopic meniscal repair: a meta-analysis. J Orthop Traumatol. 2022;23:8. Source
- Dave U, et al. Platelet rich plasma augmentation for meniscus repair reduces failure but not complication rates or outcomes: a systematic review and meta-analysis. J Orthop. 2025;73:62–71. Source
Medically reviewed by Paul N. Morton, MD, FAAOS, FAAHKS — board-certified orthopedic surgeon, fellowship-trained in adult hip & knee reconstruction and orthopedic trauma. Last reviewed: .
This page is for education only and isn’t a substitute for an exam and personalized advice — schedule a consultation to discuss your situation.